

October 29, 2026 · 18 min read
Knee Effusion in Dallas: A Cause-First Guide to Evaluation and Non-Surgical Options
Medically reviewed content from RegenOrthoSport, Dallas, Texas.
Start with what knee effusion means
A knee effusion is an abnormal accumulation of fluid within the knee joint. You may describe the result as a swollen knee or fluid on the knee, but the finding itself does not identify the cause.
Several conditions can produce fluid in the joint. Traumatic injuries, inflammatory conditions, infection, and degenerative changes such as osteoarthritis are all possible categories. Osteoarthritis may be part of the picture, especially when swelling appears during a flare, but swelling alone cannot establish that explanation.
The practical question is not which treatment name sounds appropriate first. The practical question is what the swelling pattern, symptoms, history, examination, and broader health factors suggest about the next evaluation step. A cause-focused approach helps separate situations that need prompt medical attention from those that may allow a planned assessment. It also keeps discussions of non-surgical treatments in the right order: evaluation first, treatment options second.
For you, that means recording what changed, how quickly it changed, what you can and cannot do with the knee, and whether the swelling has returned before. Those details give a clinician a clearer starting point than the label alone.
At a consultation, ask what a proposed examination or test is intended to clarify and which questions its results may answer. The same amount of visible swelling can lead to different questions depending on whether it followed trauma, appeared during an osteoarthritis flare, or developed with heat and restricted movement. The next step should follow that pattern.
Use the swelling pattern to decide how quickly to act
After an injury, severe pain, immediate swelling, instability, or inability to bear weight warrant urgent medical evaluation. Certain combinations should not wait for a routine conversation.
A knee that becomes acutely hot, red, and difficult to move also raises concern for septic arthritis, particularly when the change affects one joint.
These findings can occur with joint infection. Fever does not need to be present for infection to deserve consideration, so do not use the absence of fever as a reason to dismiss a rapidly worsening joint.
When an injury has not occurred and none of these warning patterns is present, the cause still cannot be identified from swelling alone. Persistent, recurring, or unexplained fluid can have different causes, and care depends on which cause is found. If your ability to walk or move the knee changes quickly, move from routine planning to prompt evaluation.
Use the timing of the change as part of your decision. Immediate swelling after trauma, a rapidly worsening joint, or a sudden loss of movement calls for a different level of attention than a gradual pattern that has remained stable. When you are uncertain about the urgency, describe the change and the associated symptoms to a healthcare professional rather than relying on appearance alone. That description is most useful when it separates the knee’s baseline from the new event. Explain whether swelling followed an injury, whether it appeared immediately or over time, and whether movement or weight-bearing changed at the same time. Also note whether the joint became hot or red, whether symptoms are worsening, and whether this episode resembles prior osteoarthritis flare-ups. These observations do not establish a diagnosis. They help communicate the combination and sequence of findings that determines whether the situation needs prompt attention or a non-urgent evaluation.
Do not assume osteoarthritis explains every swollen knee
Osteoarthritis can be associated with knee swelling, but osteoarthritis is only one possible explanation. Fluid can follow an injury, reflect an inflammatory condition, occur with infection, or accompany degenerative changes in the knee.
Osteoarthritis flare-ups, repetitive overuse, and degenerative meniscal tears can all be associated with an effusion. A pattern that develops gradually with activity may fit a different clinical question from swelling that appears immediately after a fall or twisting event. A recurring pattern may also prompt a different evaluation from a single episode that follows a clear injury.
You should therefore describe the pattern instead of presenting osteoarthritis as an established cause. Note whether the swelling began suddenly or gradually, whether it followed a specific event, and whether it has appeared after repeated activity. Record changes in motion, walking, locking, popping, or giving way. These details do not diagnose the problem, but they help a clinician decide which structures and causes deserve attention.
The same principle applies when an imaging report already mentions arthritis. An imaging label can be part of the clinical picture without explaining every new change in swelling or function. If the symptoms do not match your prior pattern, mention that difference directly during evaluation.
A history of osteoarthritis can make a flare seem familiar, but familiarity should not erase a change in pattern. Tell the clinician if swelling is more sudden, lasts longer, returns more often, or affects movement differently than before. That comparison can help frame the evaluation without turning your own observation into a diagnosis. Consider making a simple comparison with your usual knee pattern: what is familiar, what is new, and what has lasted longer or returned more often. This comparison is especially useful when an older imaging report or prior osteoarthritis diagnosis makes the explanation feel obvious. The purpose is not to challenge the prior diagnosis or assign a new one. It is to show whether the present episode follows the pattern that has already been evaluated. A change from baseline can help the clinician decide which history questions, examination findings, or tests deserve attention.
Prepare for a cause-focused evaluation
A cause-focused knee evaluation starts with your history and a physical examination. The clinician will use the pattern of symptoms and findings to decide whether additional testing may help.
Prepare to explain:
- When the swelling began and whether it appeared suddenly or gradually.
- Whether a fall, twist, impact, or other event preceded it.
- Whether the swelling has recurred and how long each episode lasts.
- Where symptoms occur and what activities change them.
- Whether the knee locks, pops, gives way, or feels unstable.
- Whether you can bear weight and move the knee through its usual range.
- What care you have already tried and what happened afterward.
An examination may include inspection, palpation, assessment of the fluid and range of motion, and checks of the ligaments and menisci. The clinician may also consider the knee’s structure, possible causes, and broader health factors before choosing a next step.
Radiographs may be considered in selected situations. AAFP guidance identifies inability to bear weight, inability to flex the knee to 90 degrees, isolated tenderness near the kneecap or fibular head, and age over 55 among situations in which radiographs are indicated. That guidance does not mean every person with swelling needs the same imaging. It means the examination and history help connect an imaging decision to a specific clinical question.
Bring prior records if you have them, but do not assume an old image explains a new episode. Ask what question each proposed test is intended to answer.
A useful evaluation conversation separates three questions: what may be happening, whether additional testing can clarify it, and what care follows from the findings. Keeping those questions separate can prevent a treatment discussion from moving ahead before the swelling has been assessed. You can use the same separation when reviewing a proposed test. First ask what finding prompted it. Next ask what result would add to the history and examination. Finally ask what decision would change if the result were positive, negative, or inconclusive. This does not mean you need to choose tests yourself. It gives you a way to understand why imaging, examination, or fluid assessment is being considered. It also helps prevent a familiar label such as osteoarthritis from becoming the only question under discussion.
Know when fluid testing may change the next step
Knee aspiration is a procedure a clinician may use to help evaluate or treat selected conditions, including an unexplained effusion or a large effusion causing symptoms. Aspiration removes joint fluid for assessment and may also provide relief when the amount of fluid is substantial.
Fluid testing becomes especially relevant when infection or crystal-related inflammation is part of the clinical question. When septic arthritis is suspected, synovial-fluid testing and culture help identify infection and guide treatment. The result is not interpreted in isolation; symptoms, examination findings, and the rest of the clinical picture still matter.
A clinician may also consider aspiration when the cause of the fluid is unclear, when blood in the joint is suspected, or when a large collection is interfering with movement. A large effusion can recur, and repeat aspiration may sometimes be needed. Recurrence is therefore a reason to revisit the cause rather than treating each episode as an unrelated event.
Whether aspiration or an injection is appropriate depends on clinical circumstances, including infection risk and joint accessibility. Do not treat a procedure as an automatic response to swelling. Ask what question the procedure is meant to answer, whether fluid will be sent for testing, and how the result would change the next step.
Fluid testing can change the direction of care because it may help distinguish among different explanations for swelling. That does not make aspiration necessary for every swollen knee. It makes the reason for the procedure worth understanding before you agree to it, particularly when infection or another condition requiring specific treatment is being considered. A useful distinction is whether aspiration is being discussed to obtain information, reduce pressure from a large effusion, or address both purposes. Ask whether the fluid will be analyzed, which question the analysis is intended to answer, and how the result affects subsequent care. If the fluid returns, ask whether recurrence changes the evaluation. These questions do not tell you whether aspiration is appropriate; they clarify its role in the cause-focused plan and keep a procedure from being treated as a substitute for understanding the swelling.
Match care to the underlying cause
Care for fluid in the knee depends on the underlying cause. Treating that cause may reduce the swelling, while some situations require symptom management rather than eliminating the fluid entirely.
That distinction changes the conversation. A clinician may focus on identifying an injury, inflammatory condition, infection, crystal-related problem, or degenerative change before discussing a longer-term plan. If infection is a concern, evaluation and treatment for infection take priority over a routine discussion of regenerative options. If a large unexplained effusion is present, aspiration or fluid testing may answer a more immediate question than an elective treatment discussion.
Clinicians may consider anti-inflammatory medication for joint inflammation and fluid accumulation after assessing your individual situation. Medication choice depends on clinical factors that are not available from a general article, so do not treat a medication category as a personal recommendation.
A cause-first plan also gives you a clearer way to judge proposed care. Ask which finding the treatment is intended to address, whether the cause has been sufficiently evaluated, what alternatives remain, and what uncertainty still applies. The answer should connect the proposed care to your symptoms and findings rather than to the presence of fluid alone.
If the swelling keeps returning, report that pattern. Recurrence can change the evaluation question and may call for a renewed discussion of the underlying cause.
Make the consultation record the starting point: note when swelling began, whether it has recurred, any injury mechanism, locking or giving way, changes in motion or ability to bear weight, and prior management. Then ask which possible cause is being evaluated, whether examination or testing may clarify it, and how each proposed option relates to the findings. This record keeps the discussion focused on your history and the clinical picture, not on fluid alone. Before discussing a longer-term option, ask the clinician to state its target in plain language: which symptom, finding, or suspected condition is it intended to address? Then ask what other options remain, what uncertainty applies, and what new information would change the plan. A clear answer should connect the option to the evaluation rather than simply to the presence of fluid. If the cause remains unclear, that uncertainty belongs in the decision. Recognizing an unresolved question is useful information, not a reason to force a treatment choice.
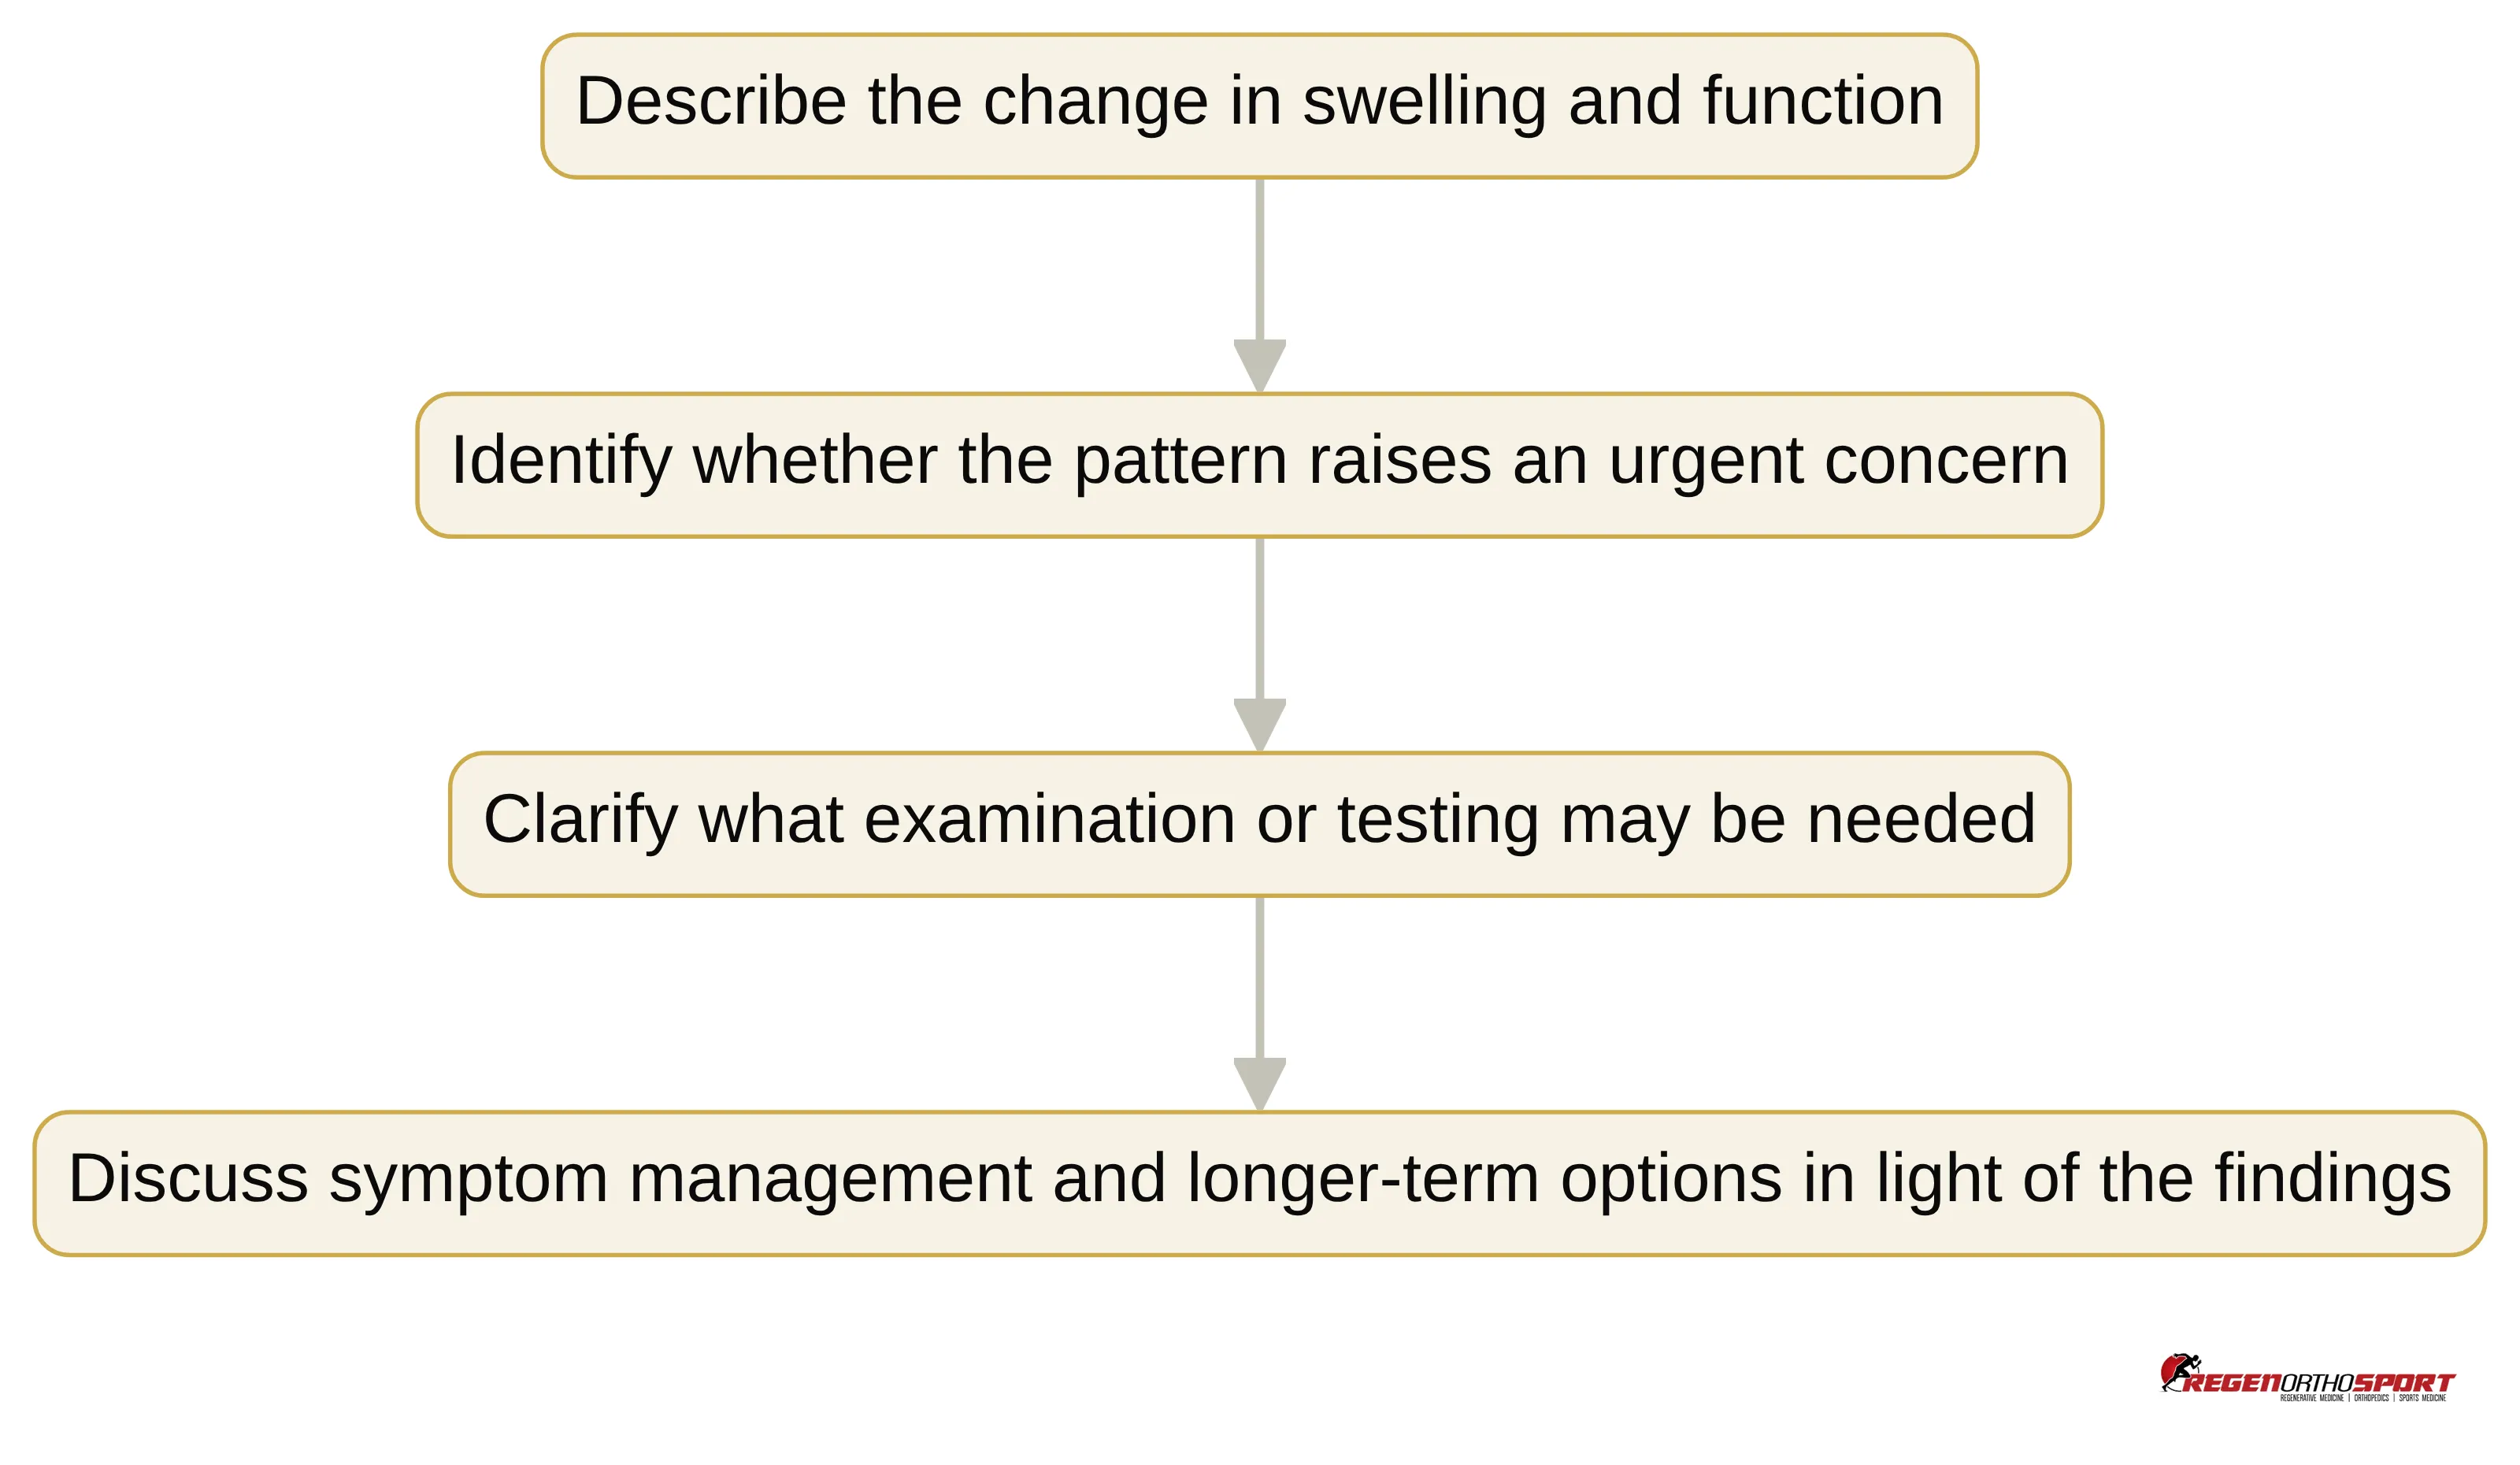
Place PRP therapy and stem cell therapy after evaluation
PRP therapy and stem cell therapy belong after evaluation, not before the cause of the swelling has been considered. A fluid-filled knee can reflect several different conditions, so the finding alone does not establish that either option fits your situation.
A Dallas consultation may discuss whether PRP therapy, stem cell therapy, or another non-surgical treatment warrants consideration based on your symptoms, suspected condition, prior care, goals, evidence limits, and practical circumstances. That discussion is different from selecting a procedure from a symptom label. It should address what is known about the condition, what remains uncertain, and what question the proposed treatment is meant to address.
Your goals also matter. You may want to walk more comfortably, return to a preferred activity, manage recurring swelling, or understand options before making a decision. State the goal clearly, then ask how the proposed option relates to it. A treatment conversation should not bypass evaluation of warning signs, unexplained swelling, or a rapidly changing pattern.
You can use these questions to keep the discussion specific:
- What cause or condition is being considered?
- What findings support discussing this option?
- What other non-surgical approaches should be considered?
- What evidence applies to this condition, and what remains uncertain?
- How would the plan change if swelling returns or new symptoms appear?
The purpose of these questions is to support an informed discussion, not to predict an individual result.
A consultation about regenerative medicine is therefore one part of a broader care decision. It may be relevant when you want to discuss PRP therapy or stem cell therapy, but it does not replace assessment of the swollen joint. The treatment name should come after the clinical question, not stand in for it.
Use evidence limits to frame the regenerative discussion
The evidence discussion for regenerative medicine needs careful wording. The American Academy of Orthopaedic Surgeons says evidence for orthopaedic stem cell treatments remains limited and that some products may carry significant risks; few products meet rigorous FDA safety and effectiveness criteria.
At the same time, AAOS lists early knee osteoarthritis among proposed orthobiologic uses. That listing describes a proposed use. It does not establish that a particular treatment will help you, explain every cause of swelling, or settle whether a procedure fits your circumstances.
Those statements can both shape a responsible consultation. A proposed use gives you a topic to discuss. Limited evidence means you should ask for the specific condition, product or procedure being discussed, available supporting evidence, known risks, and the limits of what can be concluded. The conversation should also distinguish a treatment discussed for early osteoarthritis from treatment considered for an unexplained or actively inflamed joint.
Avoid judging an option by a broad label such as regenerative treatment. Ask for the narrower description. You should understand what is being proposed, why it is being proposed for your clinical picture, what evidence supports that use, and what findings would change the plan.
No discussion of PRP therapy or stem cell therapy can replace prompt assessment of a hot, red, difficult-to-move joint or swelling after acute trauma with instability or inability to bear weight. Those patterns call for the appropriate level of medical evaluation first.
The most useful question is not whether a treatment has a positive or negative label. Ask what exact condition, preparation, or procedure is under discussion and what conclusion the supporting evidence can reasonably support. This keeps proposed use, clinical uncertainty, and your own decision separate. Use that separation when comparing information from a consultation with general claims about regenerative medicine. A broad statement about possible use does not answer whether the evidence applies to your type of knee problem, the specific preparation or procedure, or the current state of the joint. Ask which part of the discussion is established, which part is proposed, and which part remains unknown. You can then weigh the option alongside other non-surgical approaches without treating uncertainty as either proof of benefit or proof that discussion is pointless.
Bring a focused consultation record
A focused consultation record helps you describe the knee without relying on memory alone. The most useful record connects the swelling pattern to your symptoms, prior care, goals, and practical questions.
Write down:
- The date or approximate timing when swelling began.
- Whether the change followed an injury, repeated activity, or no clear event.
- Whether the swelling has recurred, and how the episodes compare.
- Changes in walking, weight-bearing, range of motion, locking, popping, or giving way.
- The location and character of your symptoms.
- Care you have already tried and the response you noticed.
- Relevant health factors that may affect an evaluation or treatment discussion.
- Your main functional goal for the consultation.
You can also bring a short list of questions. Ask what cause is being considered, whether fluid testing or imaging would change the next step, and how the proposed care relates to your findings. If you want to discuss PRP therapy or stem cell therapy, ask what evidence limits apply to your condition and what other non-surgical options belong in the conversation.
A Dallas consultation can consider symptoms, suspected condition, prior management, goals, evidence limits, and practical circumstances. Providing those details in an organized form makes the discussion more concrete. It also helps separate a question about diagnosis or evaluation from a question about elective treatment.
Keep the record focused on change over time. A short timeline showing when swelling appeared, what preceded it, how movement changed, and whether it returned can be more useful than a long list without dates or sequence. Bring imaging or prior treatment information when available, and ask how each item affects the question being discussed. One practical format is a short timeline with four entries: the first noticeable change, what happened immediately before it, what changed in movement or daily activity, and whether swelling returned. Add questions beside the relevant entry—for example, whether a recurring episode changes the evaluation or whether a prior treatment response matters. Keep observations separate from conclusions: record that the knee felt warm or that walking changed, rather than deciding what those details mean. This makes the record easier to review and leaves diagnosis to the clinician.
Know what a Dallas consultation can and cannot decide
A Dallas consultation can organize a discussion about whether PRP therapy, stem cell therapy, or another non-surgical treatment warrants consideration. We base that discussion on your symptoms, suspected condition, prior care, goals, evidence limits, and practical circumstances.
The consultation can help you clarify:
- Which part of your history needs more attention.
- Whether the proposed treatment matches the condition being discussed.
- What uncertainty applies to the available evidence.
- Which questions remain before you decide on a treatment path.
- What practical factors may affect the discussion.
A consultation cannot turn swelling into a diagnosis by itself, and it cannot establish individual eligibility, candidacy, or prognosis from the finding alone. Warning signs also change the priority of the conversation. A rapidly hot, red, difficult-to-move joint or an injured knee with instability or inability to bear weight needs the appropriate medical evaluation rather than a routine procedure discussion.
Use the appointment to ask for a clear explanation of the reasoning. You can ask what information supports the proposed option, what information is still needed, and what would lead the clinician to recommend a different next step. This keeps the decision connected to your clinical picture instead of to a treatment name.
The consultation is most useful when you bring both medical and practical questions. You can discuss the pattern of swelling, your functional goal, prior care, evidence limits, and the circumstances that affect your decision. The appointment can organize those topics, but it does not remove the need for clinical judgment about your individual situation. Before scheduling, use the consultation’s boundaries as a decision check. If the knee has an urgent warning pattern, prioritize the appropriate medical evaluation. If the pattern has already been assessed and you want to discuss non-surgical options, bring the findings that support that discussion. If the cause remains uncertain, make that uncertainty one of your first questions. This helps you choose an appointment for the question you actually need answered, rather than assuming that a consultation or a treatment name can answer every question about swelling.
Confirm location and payment expectations before scheduling
We provide consultations and procedures at our Dallas office and serve patients from across Dallas–Fort Worth. That location is relevant when you are weighing travel, appointment timing, and follow-up logistics.
We are a self-pay practice. Our regenerative procedures are not billed to insurance and are not reimbursable by Medicare. Plan for that distinction before you make a financial decision about care.
We provide a clear quote after your complimentary consultation and before scheduling. We also offer an in-house payment plan and monthly payment plans through Cherry. These details give you a practical framework for discussing cost after the clinical conversation, without treating a price estimate as a reason to skip evaluation.
Bring payment questions to the consultation alongside your health questions. You can ask which service the quote covers, when payment would be due, and how a proposed plan relates to the discussion you had. The clinical decision and the financial decision are connected in practical terms, but they should remain separate questions: first understand what is being considered, then understand the associated cost and payment arrangement.
Dallas–Fort Worth location and self-pay status are practical parts of deciding whether a consultation fits your circumstances. Include travel, scheduling, and payment questions in your planning rather than treating them as details to address after a procedure has been selected.
Choose the next step for your swollen knee
Your next step should match the swelling pattern, accompanying symptoms, and information you already have.
- Choose urgent medical evaluation if swelling follows an injury with severe joint symptoms, immediate swelling, instability, or inability to bear weight. Seek prompt evaluation for a hot, red, difficult-to-move joint or swelling with fever, warmth, severe joint symptoms, or marked loss of motion.
- Record whether the swelling persists, returns, or has no clear explanation. Bring the timing, injury history, motion changes, mechanical symptoms, prior care, and functional goals.
- Discuss non-surgical options after evaluation if you want to understand whether PRP therapy, stem cell therapy, or another option belongs in your care conversation. Ask how the proposed treatment relates to your suspected condition, goals, evidence limits, and practical circumstances.
A qualified healthcare professional must decide which evaluation and treatment options fit your circumstances. The goal is a clear, cause-focused decision rather than a conclusion based on swelling alone.
Choose the next conversation that matches your urgency, then bring your focused questions and treatment goals with you.
Questions to ask before discussing regenerative treatment
What does a knee effusion indicate?
A knee effusion refers to an abnormal accumulation of fluid within the knee joint, which can result from traumatic injuries, inflammatory conditions, infections, or degenerative changes like osteoarthritis.
When should I seek urgent medical evaluation for knee swelling?
Urgent evaluation is necessary if swelling follows an injury and is accompanied by severe symptoms, immediate swelling, instability, or inability to bear weight. Also, seek prompt care for a hot, red, difficult-to-move joint or swelling with fever.
What should I prepare for a knee evaluation consultation?
Prepare to discuss when the swelling began, any preceding events, recurrence patterns, changes in movement, and previous treatments tried. This information helps the clinician assess your condition effectively.
How does treatment for knee effusion vary based on its cause?
Treatment depends on the underlying cause of the effusion. Some causes may resolve with treatment, while others may require ongoing symptom management rather than eliminating the fluid.
What role do PRP therapy and stem cell therapy play in treating knee effusion?
PRP therapy and stem cell therapy should be discussed after evaluating the cause of the effusion. These treatments may be considered based on individual symptoms and clinical findings.
What are the payment expectations for treatments at RegenOrthoSport?
RegenOrthoSport operates as a self-pay practice, meaning regenerative procedures are not billed to insurance and are not reimbursable by Medicare. A clear quote will be provided after the consultation.
What information should I bring to a consultation about knee effusion?
Bring a record of your symptoms, any changes in knee function, previous treatments, and your main goals for the consultation. This helps facilitate a focused discussion about your care options.